Medically Reviewed By Dr. Magnus Jayaraj Mansard. Specialist in Liver Transplantation, HPB Surgery and Surgical Gastroenterology. Last Medically Reviewed: October 2026
If you have been told that you have fatty liver, you may come across terms such as NAFLD, NASH, MASLD and MASH. These terms can be confusing, especially because medical terminology for fatty liver disease has changed in recent years.
NAFLD (non-alcoholic fatty liver disease) and NASH (non-alcoholic steatohepatitis) are older terms. Today, NAFLD is generally referred to as MASLD (metabolic dysfunction-associated steatotic liver disease), while NASH is now called MASH (metabolic dysfunction-associated steatohepatitis). The updated terminology was introduced to better describe the metabolic factors associated with fatty liver disease.
For people searching specifically for “NASH vs NAFLD,” the important point is this: fat in the liver does not always mean that inflammation or liver injury is present. Some people have liver fat without significant inflammation, while others develop inflammation and liver-cell injury that can lead to fibrosis or cirrhosis.
Quick Answer: NASH vs NAFLD
NAFLD was the older term for fatty liver disease associated with little or no alcohol use. NASH was a more active form of NAFLD in which liver fat was accompanied by inflammation and liver-cell injury.
Today:
- NAFLD → MASLD
- NASH → MASH
- Fatty liver disease → Steatotic liver disease (SLD) as the broader category
MASLD is associated with metabolic risk factors such as excess body weight, insulin resistance, type 2 diabetes, high blood pressure and abnormal cholesterol levels. MASH refers to MASLD in which inflammation and liver-cell injury are present.
What Is NAFLD or MASLD?
NAFLD was previously used to describe excess fat accumulation in the liver when significant alcohol consumption was not considered the main cause.
The newer term, metabolic dysfunction-associated steatotic liver disease (MASLD), focuses more on the underlying metabolic factors.
MASLD can occur in people with:
- Overweight or obesity
- Increased abdominal fat
- Prediabetes or type 2 diabetes
- High blood pressure
- High cholesterol or triglycerides
- Insulin resistance
- Low physical activity
A person can have MASLD without feeling unwell. In fact, many people discover it during a routine health check, ultrasound or blood test.
Having fatty liver does not automatically mean that severe liver damage is present. The more important question is whether there is liver inflammation or fibrosis (scarring).
What Is NASH or MASH?
NASH is the older name for metabolic dysfunction-associated steatohepatitis, now called MASH.
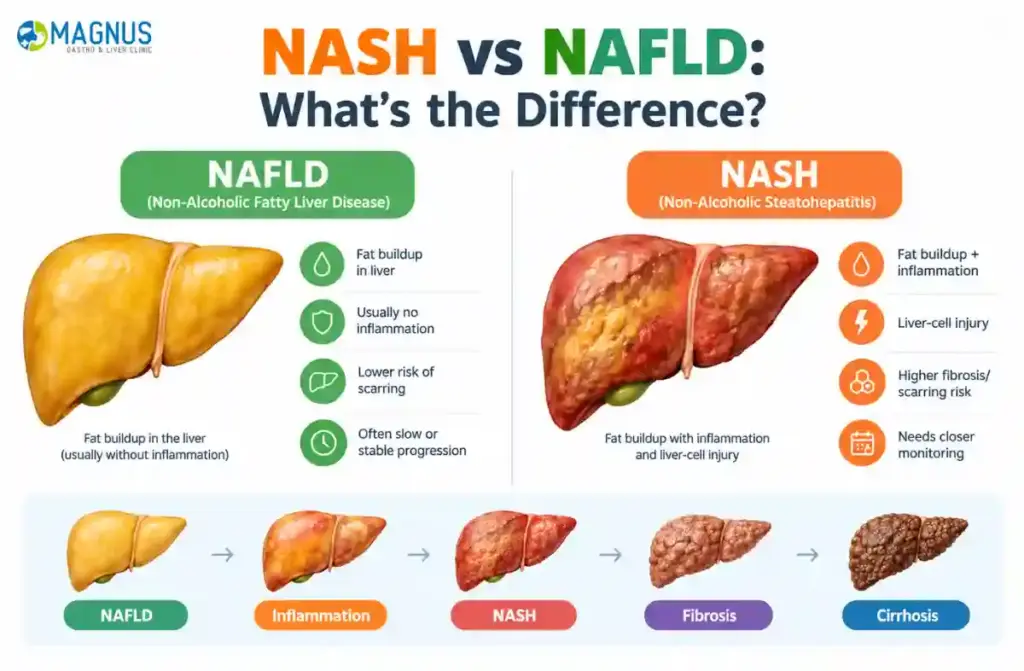
MASH occurs when excess liver fat is associated with inflammation and liver-cell injury. In some people, continued inflammation can contribute to progressive fibrosis.
Fibrosis means scar tissue develops in the liver. Advanced fibrosis can eventually lead to cirrhosis, which can impair liver function and increase the risk of complications.
However, not everyone with MASLD develops MASH, and not everyone with MASH develops cirrhosis.
The risk of progression varies from person to person and depends on factors including metabolic health, diabetes, body weight, genetics and the amount of liver fibrosis already present.
NAFLD vs NASH: Key Differences
| Feature | NAFLD | NASH |
| Older terminology | Non-alcoholic fatty liver disease | Non-alcoholic steatohepatitis |
| Current terminology | MASLD in appropriate patients | MASH |
| Liver fat | Present | Present |
| Liver inflammation | May be absent | Present |
| Liver-cell injury | May be absent | Present |
| Fibrosis risk | Variable | Higher concern |
| Monitoring | Depends on individual risk | Usually requires closer assessment |
| Potential progression | May remain stable or progress | Can progress to significant fibrosis and cirrhosis |
One important clarification is that NAFLD was not simply a disease with “no inflammation.” It was a broader older classification. The modern MASLD/MASH terminology provides a more precise way of describing the disease spectrum.
MASLD vs MASH: The New Terminology
If your old medical report says NAFLD or NASH, you may see MASLD or MASH used during a newer consultation. The change does not mean that the disease itself suddenly changed.
Instead:
NAFLD is now generally called MASLD when the person has hepatic steatosis along with relevant cardiometabolic risk factors.
NASH is now called MASH when metabolic dysfunction-associated steatotic liver disease includes steatohepatitis, meaning inflammation and liver-cell injury.
The broader term steatotic liver disease (SLD) includes different causes of liver fat accumulation. These can include metabolic causes, alcohol-associated disease and other less common causes.
This updated terminology is important when reading newer medical information or discussing your diagnosis with a liver specialist.
What Causes MASLD and MASH?
Fatty liver disease is closely associated with metabolic health.
Common contributing factors include:
- Excess body weight: Extra body fat, particularly abdominal fat, can increase the risk of metabolic dysfunction and liver fat accumulation.
- Insulin resistance and diabetes: Insulin resistance and type 2 diabetes are important risk factors for MASLD and progression to more advanced liver disease.
- High cholesterol and triglycerides: Abnormal blood lipid levels can be associated with increased liver fat and cardiovascular risk.
- High blood pressure: Hypertension commonly occurs alongside the metabolic conditions associated with MASLD.
- Physical inactivity: A sedentary lifestyle can contribute to weight gain, insulin resistance and metabolic dysfunction.
- Genetic and other factors: Family history, genetics, age and other medical conditions can influence an individual’s risk and disease progression.
Because MASLD is strongly connected with metabolic health, treatment should not focus only on the liver. Blood sugar, cholesterol, blood pressure, body weight and cardiovascular risk should also be addressed.
What Are the Symptoms of MASLD or MASH?
Many people with MASLD have no obvious symptoms, especially during the early stages.
Some people may experience:
- Tiredness
- A feeling of discomfort in the upper-right abdomen
- General weakness
- Abnormal liver enzyme results found during routine testing
Symptoms alone cannot reliably tell whether someone has simple liver fat, MASH or advanced fibrosis. This is why medical assessment and fibrosis risk evaluation are important.
How Is NAFLD, MASLD, NASH or MASH Diagnosed?
Diagnosis usually involves several pieces of information rather than one test.
- Blood tests: Blood tests may include liver enzymes such as ALT and AST, platelet count, blood sugar and lipid testing. Doctors may also check for other causes of liver disease when appropriate.
- Ultrasound: An abdominal ultrasound can identify features suggesting fatty liver, although it does not determine the exact degree of inflammation or fibrosis.
- FibroScan or elastography: Elastography can help assess liver stiffness and estimate the likelihood of significant fibrosis without requiring a biopsy.
- FIB-4 score: The FIB-4 index is a commonly used non-invasive tool for assessing the risk of advanced liver fibrosis. It uses factors such as age, AST, ALT and platelet count. Depending on the result and the person’s clinical situation, additional testing may be recommended.
- MRI-based testing: In selected patients, MRI-based techniques can provide additional information about liver fat and fibrosis.
- Liver biopsy: A liver biopsy is not required for every person with fatty liver. It may be considered when non-invasive tests are inconclusive or when a precise assessment of liver injury is necessary.
Can Fatty Liver Turn Into NASH?
Yes, some people with fatty liver can develop MASH, but progression does not occur in everyone.
The risk may be higher in people with:
- Type 2 diabetes
- Obesity or significant abdominal fat
- Insulin resistance
- High triglycerides
- Metabolic syndrome
- Other risk factors for progressive liver disease
The presence and severity of fibrosis are particularly important when assessing long-term liver risk.
This is why simply knowing that an ultrasound shows “fatty liver” may not be enough. Your doctor may need to determine whether there is significant fibrosis.
Can NASH or MASH Cause Cirrhosis?
MASH can contribute to progressive liver fibrosis in some people.
The progression generally occurs over time:
Liver fat → inflammation and liver-cell injury → fibrosis → advanced fibrosis → cirrhosis
This is not an inevitable pathway. Many people with fatty liver do not progress to cirrhosis.
Early identification of people at higher risk allows doctors to focus on metabolic risk factors, lifestyle changes and appropriate medical monitoring.
How Is MASLD and MASH Treated?
Treatment depends on the person’s metabolic health, degree of liver damage and fibrosis risk.
Weight management
For people who are overweight or have obesity, gradual and sustained weight loss can reduce liver fat and improve metabolic health.
Evidence shows that losing around 3–5% of body weight can reduce liver fat, while greater weight loss may provide additional benefits for liver inflammation and fibrosis.
The goal should be individualized rather than based on a single number for everyone.
Healthy eating
A sustainable eating pattern is generally more useful than following a short-term “liver detox.”
A balanced diet can include:
- Vegetables
- Fruits in appropriate portions
- Whole grains
- Legumes
- Nuts and seeds
- Fish or other healthy protein sources
- Unsaturated fats
Reducing excess calories, sugary drinks, refined carbohydrates, saturated fats and highly processed foods may be helpful.
Regular physical activity
Exercise can improve metabolic health and reduce liver fat.
A practical target often used in clinical guidance is around 150 minutes of moderate physical activity per week, adjusted according to a person’s health and physical ability.
A combination of aerobic activity and resistance exercise can be useful.
Control diabetes, cholesterol and blood pressure
Treating associated metabolic conditions is an important part of MASLD management.
Your doctor may recommend medications for diabetes, cholesterol or blood pressure when appropriate.
Medical treatment
Some patients with MASH and significant fibrosis may be candidates for specific pharmacological treatments. Treatment choices depend on fibrosis stage, metabolic conditions, other medications and individual risks.
For example, AASLD guidance has been updated regarding the use of semaglutide in selected patients with MASH and moderate-to-advanced fibrosis.
Medication should be prescribed based on a medical evaluation rather than used solely because an online article recommends it.
Can MASLD or MASH Be Reversed?
In many people, improving metabolic health can reduce liver fat and may improve inflammation and, in some cases, fibrosis.
Lifestyle changes are therefore an important part of treatment.
However, “reversal” should not be assumed from an improvement in liver enzymes or a single ultrasound. Liver health needs to be assessed using the appropriate combination of clinical evaluation, blood tests and fibrosis assessment.
The earlier significant risk is identified, the more opportunities there may be to prevent further progression.
When Should You See a Liver Specialist?
Consider discussing fatty liver with a gastroenterologist or hepatologist if:
- You have persistent elevation of liver enzymes
- An ultrasound shows fatty liver
- You have diabetes or multiple metabolic risk factors
- You have been told you have liver fibrosis
- Your FIB-4 or elastography suggests increased fibrosis risk
- You have abnormal liver function tests
- You have symptoms or signs suggesting advanced liver disease
- You are unsure whether your fatty liver requires follow-up
A specialist can help determine whether you have uncomplicated MASLD, MASH or a more advanced stage of liver disease.
Key Takeaway
If you search for NASH vs NAFLD, remember that these are largely older terms.
NAFLD is now generally referred to as MASLD, and NASH is now called MASH.
The important distinction is not simply whether fat is present in the liver. Doctors also need to consider metabolic risk factors, inflammation, liver-cell injury and especially fibrosis.
For many people, improving body weight, physical activity, diet, blood sugar, cholesterol and blood pressure can make an important difference. People at higher risk may need additional testing and specialist follow-up.
If you have been diagnosed with fatty liver, do not assume that an ultrasound finding alone tells you how healthy or damaged your liver is. Discuss your blood tests, metabolic risk factors and fibrosis risk with a qualified gastroenterologist or hepatology specialist.
Also, Read as Life After Liver Transplant